
POST-BYPASS COMPLICATION · 5-MIN READ · UPDATED MAY 2026
GERD After Gastric Bypass: Why It Happens & What to Do
Gastric bypass is widely considered the gold-standard bariatric procedure for reflux — but in 5-10% of patients, GERD develops or persists after surgery. Here’s why.
By Dr. Alejandro López · Medically reviewed · Posted in Blog
Concerned About Your Results?
Weight regain, reflux or discomfort after bariatric surgery can be corrected. Get your case reviewed by Dr. Alejandro López — board-certified revision specialist.
GET REVIEWED BY A SPECIALIST →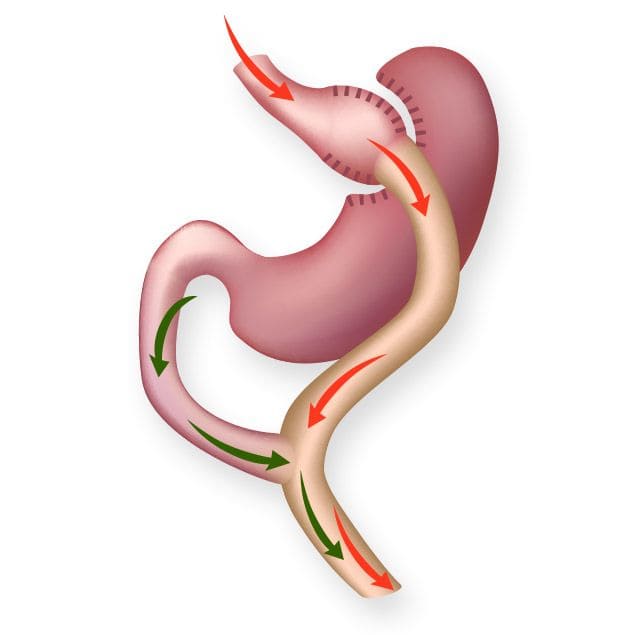
TL;DR
GERD after gastric bypass is uncommon (about 5-10% of patients) but very real when it happens. The most common causes are a large gastric pouch, recurrent hiatal hernia, weight regain, or a marginal ulcer. Treatment is targeted to the underlying cause and ranges from medication to revisional surgery.
Last resort: In very rare cases of refractory complications, gastric bypass can be reversed. See our honest guide on bypass reversal — when it makes sense, when revision is better, and the cost.
Why GERD After Bypass Is Uncommon
The Roux-en-Y bypass works for reflux because it creates a small acid-poor gastric pouch and reroutes digestive flow away from the esophagus. With this anatomy in place, there is very little acid available to reflux upward — and very little pressure pushing it that way.
So when GERD does occur after bypass, it almost always means something in that anatomy is no longer functioning as intended.
The 4 Most Common Causes
1. Large or dilated gastric pouch. The original pouch is created very small (15-30ml). Over years, with overeating or stretching, it can dilate to 60-100ml or more — producing enough acid to cause reflux.
2. Recurrent or missed hiatal hernia. Hiatal hernias can recur after bypass, or were missed at the original surgery. They allow the upper pouch to slide above the diaphragm, breaking the antireflux barrier.
3. Marginal ulcer. An ulcer at the connection between the pouch and intestine (gastrojejunal anastomosis). Causes severe pain and can mimic reflux symptoms.
4. Weight regain. Restored intra-abdominal pressure + larger pouch volume + dietary changes combine to create new reflux. Often seen 5-10 years post-bypass.
Patients Like You
Revision bypass patients treated by Dr. López in Guadalajara & Tijuana


How We Diagnose the Cause
Treatment depends entirely on the cause. Diagnostic workup includes:
- Upper endoscopy (EGD) — to visualize pouch size, look for ulcers, check anastomosis, evaluate esophagitis
- Upper GI series with contrast — to measure pouch size and detect hiatal hernia
- pH monitoring — to objectively confirm acid reflux when symptoms are atypical
- CT scan — when anatomic abnormality or internal hernia is suspected
A complete diagnostic workup typically takes 1-2 visits.
Treatment Options
Each cause has a specific treatment:
- Marginal ulcer: PPIs + sucralfate + smoking cessation. Surgery if non-healing.
- Recurrent hiatal hernia: Laparoscopic hiatal hernia repair
- Dilated pouch: Pouch revision surgery (resize) or conversion to distal bypass
- Weight regain + reflux: Distal bypass conversion or biliopancreatic diversion
For complex revision cases, a comprehensive evaluation determines the best surgical path.
When to Seek Evaluation
Schedule an evaluation if you experience:
- Reflux symptoms returning years after bypass
- New abdominal pain (especially severe or sudden)
- Weight regain combined with reflux
- Esophagitis or Barrett’s on endoscopy
- Difficulty swallowing or food sticking
Dr. Alejandro López specializes in complex bariatric revisions. Free initial evaluation available.
Frequently Asked Questions
How common is GERD after gastric bypass?
Can GERD after bypass be treated without surgery?
Does pouch dilation always cause GERD?
Will I need another revision surgery?
Concerned About Your Results?
Weight regain, reflux or discomfort after bariatric surgery can be corrected. Get your case reviewed by Dr. Alejandro López — board-certified revision specialist.
GET REVIEWED BY A SPECIALIST →Medically reviewed by Dr. Alejandro López Ortega, MD, FACS
Bariatric surgeon board-certified by the Consejo Mexicano de Cirugía General, Fellow of the American College of Surgeons and founder of ALO Bariatrics (2011), with more than 20,000 bariatric surgeries. ALO Bariatrics operates in Tijuana, Guadalajara and Puerto Vallarta, Mexico; all-inclusive packages start at $4,500 USD. Updated: 2026-06-25.